
Haglunds deformity is an enlargement of the bone at the posterior dorsal aspect of the calcaneus. It can cause problems from poor shoe fitting.
Haglunds deformity, also known as “pump bump” or “retrocalcaneal bursitis,” is a condition that affects the foot, specifically the back of the heel. It involves the enlargement and irritation of the bony prominence at the back of the heel bone (calcaneus), as well as inflammation of the surrounding soft tissues.
Haglunds deformity is characterized by the presence of a bony prominence at the back of the heel bone. This bony enlargement can be caused by a combination of factors, including a prominent heel bone structure, excessive pressure or friction on the area, and certain foot biomechanics.
The condition can cause pain, swelling, and inflammation in the back of the heel. The pain is typically worse when wearing tight or rigid shoes, such as high heels or dress shoes, which can rub against the prominent area. Activities that involve repetitive or forceful movements of the foot, such as running or jumping, may also exacerbate the symptoms.
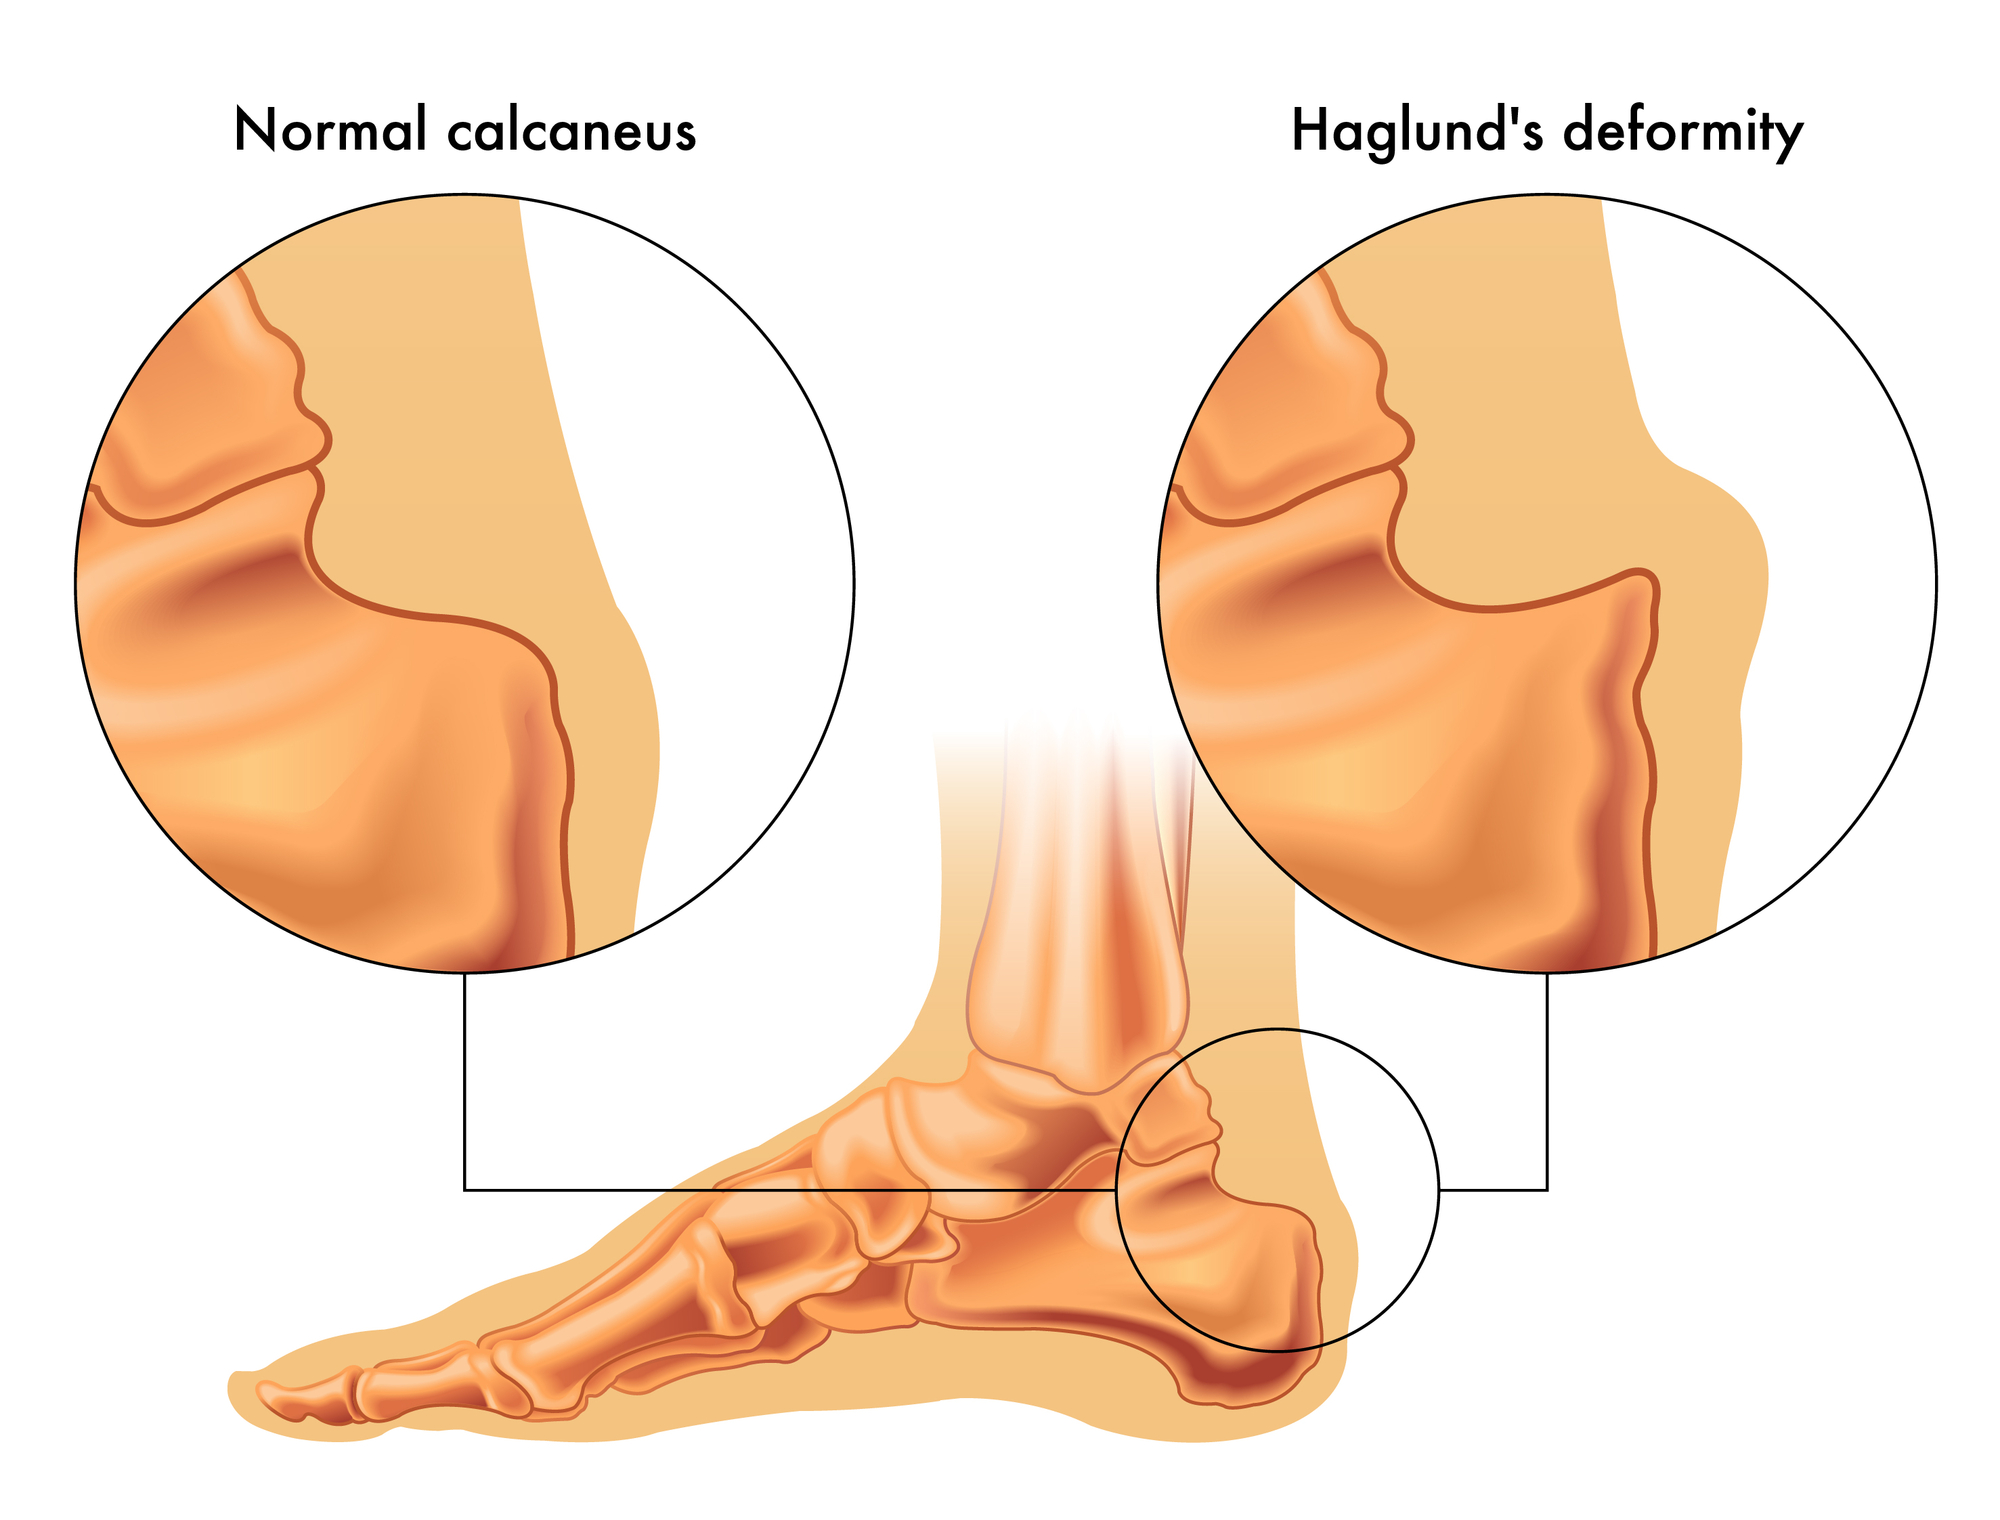
The bony prominence associated with Haglunds deformity can irritate and inflame the retrocalcaneal bursa, a fluid-filled sac located between the Achilles tendon and the calcaneus. This inflammation, known as retrocalcaneal bursitis, can cause additional pain and swelling in the area.
Haglunds deformity can develop due to a combination of factors, including inherited foot structure, abnormal foot mechanics (such as high arches or inward rolling of the foot), tight or ill-fitting shoes, and repetitive trauma to the back of the heel.
A healthcare professional, such as a podiatrist, can diagnose Haglunds deformity based on a physical examination of the foot and the patient’s medical history. X-rays or other imaging tests may be ordered to assess the bony prominence and rule out other conditions.
Treatment options for Haglunds deformity aim to alleviate symptoms, reduce inflammation, and address the underlying causes. Conservative measures include:
- Switching to footwear with open backs or low heels to reduce pressure on the area.
- Applying ice packs to reduce pain and inflammation.
- Using non-steroidal anti-inflammatory drugs (NSAIDs) to relieve pain and inflammation.
- Physical therapy exercises to stretch and strengthen the calf muscles and Achilles tendon.
- Orthotic devices or shoe inserts to correct foot mechanics and reduce pressure on the heel.
When conservative measures do not provide sufficient relief, surgical intervention may be considered. The surgical procedure may involve removing the bony prominence, reducing the pressure on the Achilles tendon, and addressing any associated soft tissue inflammation or damage.
FAQ’s on Haglunds Deformity
What is Haglunds deformity?
It is a bony prominence or ridge on the posterosuperior (upper-back) part of the heel bone. The bump itself is bone and can usually be seen and felt through the skin. Pain typically comes from the bony prominence rubbing against shoes or compressing the soft tissues (bursa and/or Achilles tendon) rather than from the bone alone. It is sometimes called a “pump bump” because rigid-backed shoes (like women’s pumps) commonly aggravate it.
What causes Haglunds deformity?
The exact cause is not fully known, but contributing factors include:
- Inherited or structural predisposition (certain shapes of the heel bone).
- High-arched (cavus) feet, which can tilt the heel and make the prominence more pronounced.
- Tight Achilles tendon or calf muscles.
- Foot mechanics such as walking on the outer edge of the foot (supination).
- Repetitive pressure or friction from rigid-backed shoes (pumps, dress shoes, boots, ice skates, some athletic shoes).
- Overuse in athletes or people who stand/walk a lot.
Genetics and foot structure appear to play a larger role than shoes alone; shoes mainly trigger or worsen symptoms.
What are the common symptoms?
- A firm, visible, and palpable bony bump on the back of the heel (often both sides).
- Pain, tenderness, redness, or swelling at the back of the heel, especially where shoes rub.
- Discomfort that worsens with closed-back or rigid shoes and improves with open-backed or soft footwear.
- Possible calluses, blisters, or skin thickening over the bump.
- Pain that may radiate or worsen with activity, walking uphill, or prolonged standing.
Some people have the bump with little or no pain.
How is it different from Achilles tendinitis or a heel spur?
Haglunds deformity involves a bony prominence that primarily causes problems through mechanical pressure (especially from shoes). Insertional Achilles tendinopathy involves degeneration or inflammation of the tendon at its attachment and may or may not include bone spurs. The two frequently coexist and can look similar, but Haglunds pain often improves markedly in open-backed shoes, while pure tendon pain may persist more with activity regardless of footwear. Imaging and a clinical exam help distinguish them. Heel spurs are also bony growths but typically form at different locations (e.g., under the heel or within the tendon insertion).
Who is most at risk?
It can affect anyone but is reported more often in women (partly linked to high-heeled or pump-style shoes), people with high arches, those with tight Achilles tendons, athletes (runners, skaters), and individuals who wear rigid-backed footwear regularly. It can appear in both younger and older adults and frequently occurs bilaterally.
How is Haglunds deformity diagnosed?
A doctor (often a podiatrist or orthopaedic foot specialist) diagnoses it through:
- History and physical exam (feeling the bump, checking for tenderness, observing footwear-related pain).
- X-rays (lateral views of the heel) to confirm the bony prominence and rule out other issues.
- Sometimes ultrasound or MRI if soft-tissue involvement (bursitis or tendon changes) needs evaluation, especially before considering surgery.
What are the non-surgical treatments?
Most people improve with conservative care:
- Footwear changes: Switch to open-backed shoes, clogs, or shoes with soft, flexible heel counters; avoid rigid backs.
- Heel lifts, pads, or cups inside shoes to raise the heel and reduce contact/friction.
- Ice, rest, and over-the-counter anti-inflammatory medications (e.g., NSAIDs) for pain and swelling.
- Physical therapy focusing on gentle Achilles/calf stretching and strengthening (avoid aggressive dorsiflexion stretches that increase impingement).
- Orthotics for high-arched feet or abnormal mechanics.
- Temporary use of a walking boot or soft cast in more severe flares.
- Other options sometimes used: shockwave therapy or carefully guided injections (e.g., into the bursa, avoiding the tendon).
Many cases improve within weeks to a few months with consistent footwear modification and these measures. The bony bump itself does not shrink, but symptoms often resolve.
When is surgery needed, and what does it involve?
Surgery is uncommon and usually reserved for cases that fail 3–6 (or sometimes up to 12) months of well-managed conservative treatment and have significant ongoing pain that limits daily activities. Procedures typically involve removing or shaving the prominent bone (calcaneoplasty or exostectomy), often with excision of the inflamed bursa. If the Achilles tendon is significantly involved, debridement and reattachment may be required. Approaches can be open or endoscopic (minimally invasive). Success rates are generally high (around 80–90% good-to-excellent results in many series).
What is the recovery like after surgery?
Recovery varies by the exact procedure:
- Simple bone removal may involve a period of limited weight-bearing or a boot for several weeks, with gradual return to normal shoes and activity over 2–3 months.
- More extensive tendon work can extend recovery to several months.
Full return to high-impact sports or heavy activity often takes longer. Physical therapy is usually part of rehabilitation. Your surgeon will provide specific timelines based on the findings and technique used.
Can Haglunds deformity go away on its own or be prevented?
The bony enlargement is structural and does not disappear without surgery. However, symptoms can resolve and stay controlled long-term with footwear changes and other conservative measures. Prevention focuses on avoiding prolonged friction: choose shoes with soft or open heel areas when possible, address tight calves, use appropriate orthotics if you have high arches, and modify activity or footwear early if a bump starts to irritate.
When should I see a doctor?
Seek evaluation if you have a painful heel bump that interferes with walking, work, or sports; if pain persists despite simple measures (shoe changes, ice, rest); or if there is significant swelling, redness, or difficulty bearing weight. Early assessment helps rule out related issues and starts effective conservative care.