
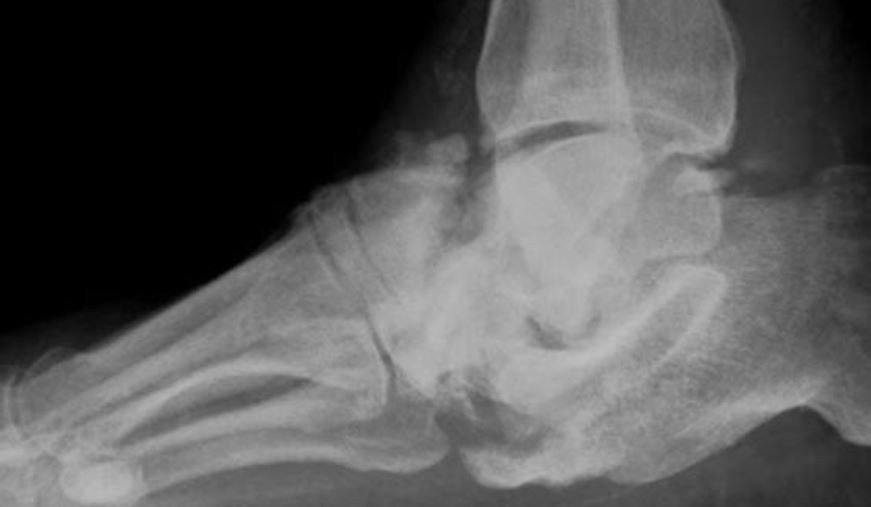
Charcot’s foot is a fracture or dislocation that occurs in medical conditions like diabetes when there is no nerve sensation to feel the trauma.
Charcot’s foot, also known as Charcot arthropathy, is a serious complication that can occur in individuals with diabetes. It is a progressive condition that affects the bones, joints, and soft tissues of the foot and ankle.
Charcot’s foot is typically associated with diabetic neuropathy, a condition characterized by nerve damage in the feet. Neuropathy can lead to a loss of sensation and proprioception (the ability to sense the position of one’s body) in the affected areas. As a result, individuals with diabetic neuropathy may continue to bear weight on their feet despite injuries or stress fractures, leading to repetitive trauma.
The exact cause of Charcot’s foot is not fully understood, but it is believed to involve a combination of factors including neuropathy, trauma, and abnormal bone metabolism. The condition often starts with an acute inflammatory phase, where there is an increased blood flow to the foot and subsequent bone resorption. Over time, this can result in the destruction of joints, fractures, and deformities.
The signs and symptoms of Charcot’s foot can vary, but they often include:
- Swelling: The foot and ankle may become swollen, red, and warm to the touch.
- Instability: The foot may lose its normal shape and structure, leading to instability and changes in gait.
- Deformities: Over time, as the bones weaken and collapse, deformities such as arch collapse, midfoot widening, and prominence of bony structures may occur.
- Lack of pain: Due to neuropathy, individuals with Charcot’s foot may not experience significant pain, even though the condition is serious and potentially debilitating.
Early detection and treatment are crucial for managing Charcot’s foot. The goals of treatment include immobilization, reducing weight-bearing on the affected foot, and preventing or correcting deformities. This is typically achieved through the use of casts, braces, orthotics, and custom shoes. In some cases, surgery may be required to stabilize the foot and correct deformities.
It’s important for individuals with diabetes, especially those with neuropathy, to carefully monitor their feet and seek immediate medical attention if they notice any signs of swelling, redness, or deformities. Regular foot examinations by a healthcare professional experienced in diabetic foot care are also essential for early detection and intervention.
The prevention and management of Charcot’s foot in diabetes involve maintaining optimal blood sugar control, practicing proper foot care, wearing appropriate footwear, and promptly addressing any foot injuries or abnormalities to prevent complications.
Charcot’s Foot FAQ:
1. What is Charcot’s Foot?
Charcot’s Foot is a destructive inflammatory condition affecting the bones, joints, and soft tissues of the foot or ankle. It occurs almost exclusively in people with peripheral neuropathy (nerve damage that reduces protective sensation). In diabetes, long-term high blood sugar damages nerves, so minor trauma or repetitive stress goes unnoticed. This triggers uncontrolled inflammation, bone resorption, fractures, and joint instability. Without treatment, the foot can collapse into a characteristic “rocker-bottom” shape.
2. Why does it happen in people with diabetes?
Diabetes is by far the most common cause because of diabetic peripheral neuropathy (sensory, motor, and autonomic). Loss of sensation means people continue walking on an injured foot. Autonomic neuropathy can increase blood flow, promoting bone breakdown. Other contributing factors include poor long-term glucose control, obesity (extra mechanical stress), smoking, longer duration of diabetes (often >7–10 years), and sometimes minor trauma or prior foot surgery/ulcer. It can rarely occur from other causes of neuropathy (e.g., alcohol-related or other neurological conditions).
3. How common is Charcot’s Foot?
It is uncommon. Estimates suggest it affects less than 1% of people with diabetes overall (range roughly 0.1–7.5% depending on the population studied, higher in those with established neuropathy). Incidence is higher in high-risk groups. Many cases are underdiagnosed or diagnosed late.
4. What are the early signs and symptoms?
Early (“active”) Charcot foot typically presents as a unilateral red, warm, and swollen foot or ankle, often with little or no pain because of the neuropathy. The affected foot feels noticeably warmer than the other. There may be mild discomfort, difficulty fitting into shoes, or subtle changes in shape. The skin is usually intact at first. These signs can easily be mistaken for infection (cellulitis), deep vein thrombosis, gout, or a sprain. Any new swelling, warmth, or redness in a neuropathic diabetic foot should raise suspicion for Charcot.
5. How is it diagnosed?
Diagnosis relies on clinical suspicion plus imaging. Doctors compare the affected foot with the opposite one for temperature difference, swelling, and redness. Plain X-rays are usually the first step (may be normal very early). MRI is more sensitive for early (stage 0) changes before bone collapse. Lab tests for infection markers are often not very helpful for distinguishing Charcot from infection. Prompt referral to a multidisciplinary diabetic foot team is recommended. Immobilization should start on clinical suspicion even before imaging confirmation.
6. What is the main treatment for active Charcot’s Foot?
Immediate and complete offloading/immobilization is the cornerstone. The preferred method is a non-removable total contact cast (TCC) or a knee-high walker made non-removable. This protects the foot, reduces inflammation, and prevents further damage while bones heal. Treatment often lasts several months (sometimes longer than for ordinary fractures). Patients usually need crutches, a knee scooter, or wheelchair and must avoid weight-bearing. Once the acute phase settles (judged by temperature normalization, reduced swelling, and stable X-rays), patients transition to custom orthotics, specialized footwear, or braces. Surgery is reserved for severe deformity, instability, or complications that cannot be managed conservatively.
7. Can Charcot’s Foot be prevented?
Risk can be reduced but not always eliminated. Key measures include:
- Excellent long-term blood glucose, blood pressure, and cholesterol control.
- Daily foot inspection (looking for swelling, redness, warmth, or shape changes).
- Regular professional foot checks (at least annually, more often if neuropathy is present).
- Proper footwear that protects and fits well; avoid going barefoot.
- Stopping smoking and maintaining a healthy weight.
- Prompt attention to any foot injury or unusual change.
8. What happens if it is left untreated or diagnosed late?
Continued walking on an active Charcot foot accelerates bone and joint destruction. This commonly leads to fixed deformity (e.g., rocker-bottom foot), high-pressure points, chronic ulcers, infection (including bone infection/osteomyelitis), and a substantially increased risk of lower-limb amputation. Early treatment can often prevent or minimize permanent deformity.
9. Will I be able to walk normally again?
With early diagnosis and proper offloading, many people retain a plantigrade (flat, walkable) foot and return to walking in specialized footwear or orthotics. Once significant deformity has occurred, walking may require custom shoes, braces, or, in some cases, reconstructive surgery. Lifelong foot protection and monitoring remain essential because the other foot is also at risk, and recurrence or contralateral involvement can occur.
10. When should I seek urgent medical attention?
Contact your diabetes or foot care team immediately (or go to urgent care/emergency if needed) if you notice:
- Unexplained swelling, warmth, or redness in one foot/ankle
- Change in foot shape or difficulty fitting shoes
- Any new wound, blister, or skin break
- Persistent warmth or swelling after minor trauma
Take the weight off the foot right away until assessed.